What the Anion Gap Shows
The anion gap is a practical way to evaluate serum electrolytes and analyze acid-base disorders. It reveals the relationship between measured cations and anions in the blood, aiding clinicians identify hidden, or unmeasured anions, that may signal a metabolic derangement. In everyday use, the Anion Gap Calculator functions as https://anion-gap-results755.tearosediner.net/how-to-operate-an-anion-gap-calculator-from-a-standard-metabolic-panel an interpretation guide for serum chemistry, not just a math tool.
At its core, the anion gap is a marker of electrolyte balance and acid-base interpretation. The most common measured components are sodium, chloride, and bicarbonate, with potassium sometimes included depending on the equation or lab method. Because the body must maintain electrical neutrality, any gap between measured positive and negative charges usually represents ions not directly reported by standard laboratory values.
That makes the anion gap a useful diagnostic clue in systemic acidosis. A widened gap may indicate excess acids or retained acids, while a low result can point to changes in protein levels, analytical issues, or less common causes involving unmeasured ions. Interpreting the result requires clinical context, because the same number can signify different things in different settings.
How to Calculate the Anion Gap
The traditional anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some formulas also include potassium, using:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Most calculators use the first version because potassium contributes less to the complete calculation in routine practice. An Anion Gap Calculator typically takes the main calculator inputs from an electrolyte panel or basic metabolic panel: sodium, chloride, bicarbonate, and sometimes potassium. Once entered, it quickly produces the calculated gap and allows faster comparison with the expected range.
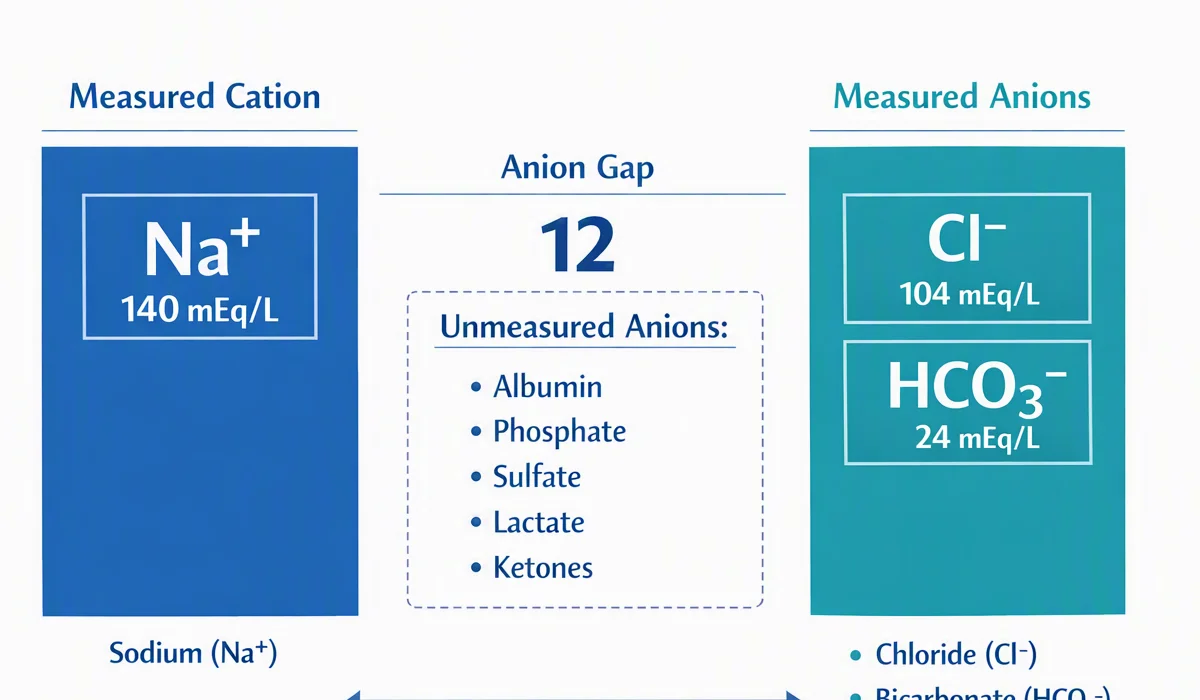
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That number alone does not diagnose a condition, but it can guide the next step in evaluation. When the gap is elevated, the clinician should consider whether the patient has a greater burden of unmeasured anions, often from acid accumulation.
Potassium may somewhat increase the numeric result when included, but the clinical interpretation usually remains largely similar. The key is consistency: use the same formula style when trending results across time or comparing them with prior laboratory values.
Standard Anion Gap Range and Reference Values
The reference range for the anion gap differs by laboratory and analyzer. That is why the reference range should always be checked against the reporting lab rather than assumed from a universal cutoff. Discrepancies in methods, ion-selective electrodes, and reporting conventions can create meaningful testing variation.
In many settings, a traditional reference interval is roughly 8 to 16 mEq/L without potassium, though some labs report different limits. The exact cutoff is less important than whether the value is above or below that lab’s stated range and whether the result fits the patient’s condition. A normal anion gap does not exclude disease, and an abnormal number does not explain the cause by itself.
Albumin also matters because it is a major negatively charged protein in plasma. Lower albumin can reduce the measured gap and make a clinically important high-gap disorder appear less dramatic. That is one reason the anion gap should be interpreted as part of a broader blood chemistry assessment rather than in isolation.
Think of the number as a moving target influenced by assay differences, protein levels, and the underlying clinical context. The most useful approach is to compare the result with the lab’s own normal interval, then decide whether correction of the anion gap is needed.
High Anion Gap Causes
A high anion gap typically indicates build-up of acid-related compounds or related acids that are not routinely measured. This pattern frequently suggests metabolic acidosis, especially when bicarbonate is low and symptoms fit an acid load. The classic concern is that extra unmeasured anions are displacing bicarbonate as buffering capacity is consumed.
Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. In lactic acidosis, lactate rises because of tissue hypoperfusion, hypoxia, seizures, severe infection, or other metabolic stress. In ketoacidosis, excess ketone bodies raise the gap, often in diabetes, starvation, or alcohol-related illness.
Renal failure can raise the anion gap when acids are not adequately excreted and retained acids accumulate. In that setting, impaired clearance contributes to renal impairment and progressive metabolic acidosis. Toxic alcohols such as methanol and ethylene glycol are especially important because they may produce a significant gap before other findings become obvious. This is where an elevated gap becomes a serious clue to toxin exposure.
Not every high gap is due to a single cause. Mixed disorders can coexist, and the degree of elevation may be blunted by low albumin. The best approach is to pair the anion gap with the full electrolyte pattern, history, and symptoms. That broader view is what makes a lab number into a clinically useful signal.
Low Anion Gap Causes
A decreased anion gap is not as frequent but still worth noting. One frequent explanation is hypoalbuminemia, since albumin adds negatively charged proteins to the blood. When albumin falls, the apparent gap falls as well, even if the true acid-base problem is not low. This is why a low number should not be overlooked automatically.
Another possibility is multiple myeloma, where abnormal proteins can disrupt charge balance and affect measured values. In some patients, positively charged paraproteins reduce the calculated gap and serve as an early clue to a plasma cell disorder. That makes the result more than just a calculation; it can become a trigger for additional testing.
Lab error is also common enough to consider first, especially if the value is surprising or inconsistent with prior results. Analytical problems, specimen issues, or transcription errors can all produce misleading results. Repeat testing is often the simplest way to confirm whether the low value is real.
Finally, unmeasured cations can lower the gap. These may include excess anion gap in chronic kidney disease lithium or other uncommon positively charged substances. In practice, the differential diagnosis of a low gap should begin with albumin, then move to measurement issues and less common clinical causes. A careful look at the full electrolyte panel is essential.
Correcting the Anion Gap for Serum Albumin
Albumin adjustment helps refine the result when serum albumin is below normal. Because albumin is a major contributor to the negative charge in plasma, low levels can hide a clinically meaningful elevation. The corrected anion gap indicates what the gap might be if serum albumin were normal.
A common approach is to add a fixed amount to the measured anion gap for each decrease in albumin below the usual reference point. Different formulas are used, so the exact adjustment may change by institution. The goal is not mathematical perfection but improved acid-base interpretation when protein levels are altered.
This is especially useful in patients with malnutrition, liver disease, inflammation, or critical illness where albumin is low. In those settings, the albumin-adjusted result may expose a hidden high gap that was masked by low protein binding. That can change how the clinician interprets the patient’s metabolic acidosis and whether additional workup is needed.
Albumin correction should be seen as part of an anion gap correction strategy, not a replacement for clinical judgment. If the corrected result is still high, it strengthens concern for true acid accumulation. If it becomes normal, the low albumin may account for much of the abnormality.
Employing an Anion Gap Calculator in clinical care
An Anion Gap Calculator can be most valuable when it is part of everyday review of the basic metabolic panel or electrolyte panel. The primary calculator inputs are straightforward, but the clinical value comes from how the result is understood. The calculator offers a quick number; the clinician supplies context.
In practice, the result helps structure the differential diagnosis. A high gap directs attention toward metabolic acidosis, while a low gap prompts review for hypoalbuminemia, analytical problems, or unusual protein or cation effects. The result becomes a quick screen for abnormalities in the body’s electrolyte balance and acid-base physiology.
Effective interpretation starts by asking a few questions: Is bicarbonate low? Is there evidence of shock, diabetes, kidney disease, or ingestion? Is albumin reduced? Are there signs of renal impairment or suspected toxin exposure? These questions keep the attention on the patient rather than the formula alone.
Strong use of an Anion Gap Calculator also means understanding trends. A rising gap may be more informative than one isolated value. Serial checks can show worsening systemic acidosis or response to treatment. That makes the calculator part of a broader monitoring strategy, not just a one-time computation.
Limitations and Common Errors
As with any lab-based test, the anion gap is subject to measurement error. Even small inaccuracies in sodium, chloride, or bicarbonate can shift the result. That is why unexpected values should be reviewed in the context of the full serum chemistry and repeated when needed.
Pseudohyponatremia can mislead the calculation if sodium is underestimated because of severe hyperlipidemia or hyperproteinemia. Since sodium is a key component of the formula, this error can skew the apparent gap. The result may look abnormal even though the underlying physiology is different.
Chloride interference is another limitation. Certain substances or analytic methods can cause chloride to be measured inaccurately, which directly affects the calculated gap. A falsely elevated chloride can make the gap appear normal even when acid accumulation is present.
Another important limitation is that the anion gap is not a direct measure of every acid. For example, beta-hydroxybutyrate may be the dominant ketone in some patients, but it is not routinely measured on standard panels. That means a clinically significant ketoacid state can exist even if the gap is only modestly changed early on. Recognizing these limitations improves both sensitivity and specificity in real-world interpretation.
When to Seek Further Evaluation
Further evaluation is warranted when the anion gap is obviously abnormal, when symptoms suggest serious illness, or when the result does not match the patient’s presentation. In those cases, an arterial blood gas or venous blood gas can provide additional insight into pH, carbon dioxide, and compensation. These tests help verify the presence and severity of acid-base disturbance.
Lactate should be checked when lactic acidosis is a concern, especially in patients with poor perfusion, infection, hypoxia, or unexplained metabolic acidosis. If ketones are suspected, targeted measurement of ketone bodies can determine the cause. If ingestion is possible, toxicology evaluation may be needed because toxic alcohols can be time-sensitive and dangerous.
The decision-making to go further should always reflect clinical context. A mild abnormality in an otherwise stable patient may need only monitoring and repeat testing. A substantially increased gap in a sick patient, however, calls for prompt workup because it may reflect a major metabolic derangement. The calculator helps spot the signal, but the bedside assessment determines urgency.
Frequently Asked Questions
What is an anion gap calculator used for?
An Anion Gap Calculator is used to promptly interpret serum electrolytes and determine whether there is an abnormal relationship of measured and unmeasured ions. It helps suggest possible acid-base disorders, especially metabolic acidosis, and can point toward causes such as lactic acidosis, ketoacidosis, or renal failure. It is best used as part of a broader clinical assessment.
How do you calculate the anion gap from serum electrolytes?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. Some formulas also include potassium, but many routine calculations do not. The inputs usually come from a basic metabolic panel or electrolyte panel. The result is then compared with the lab’s reference range or normal range.
What does a high anion gap mean?
A high anion gap usually suggests presence of unmeasured anions from acids in the blood. Common causes include metabolic acidosis, lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result is a useful diagnostic clue, but it must be interpreted with symptoms, history, and other laboratory values.
What can cause a low anion gap?
A low anion gap is most often due to hypoalbuminemia or lab error. It can also be seen with multiple myeloma or other sources of unmeasured cations. If the value is unexpected, repeating the test and reviewing the full serum chemistry is a good first step.
Should the anion gap get corrected for albumin?
Indeed, albumin correction is often useful when serum albumin is decreased. Since albumin affects the charge balance in blood, a low albumin level can obscure a true high anion gap. Using a albumin-corrected anion gap can improve interpretation, especially in patients with poor nutrition, inflammation, or other conditions affecting binding of proteins.