What the Anion Gap Indicates
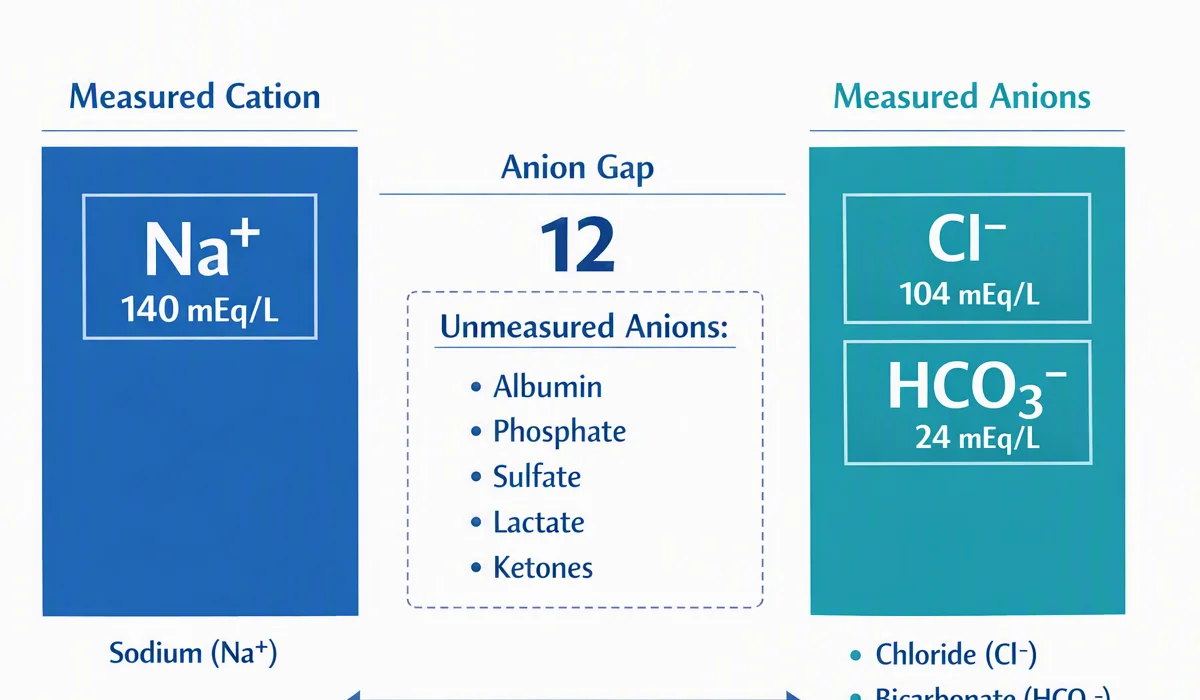
The anion gap is a derived number that assists clinicians and patients in understanding the relationship of charged particles in the blood. It is based on a standard electrolytes panel, mainly sodium, chloride, and bicarbonate. Because routine blood testing does not measure every charged molecule, the anion gap estimates the amount of unmeasured anions in the serum chemistry profile.
At its core, the anion gap reflects acid-base balance. When acids build up in the body, the gap can increase, pointing to a possible metabolic derangement. This is why the anion gap is used as a diagnostic aid rather than a standalone diagnosis. It is a form of blood test interpretation that can reveal an anion difference even when other values seem only mildly abnormal.
The basic calculation formula contrasts measured cations and anions, usually using serum sodium, serum chloride, and serum bicarbonate. The result helps clinicians understand whether there is excess acid in the blood, often from acid accumulation. In practice, the anion gap is part of a larger screening tool for evaluating unexplained symptoms, abnormal lab results, and acid-base disorders.
How to Operate an Anion Gap Calculator
An anion gap calculator streamlines the calculation and helps users promptly determine whether the result falls within the expected reference range. To use it, provide the serum sodium, serum bicarbonate, and serum albumin values if the tool includes albumin adjustment. Certain calculators also allow direct entry of serum chloride for checking the equation.
The most common formula is:
Anion gap = sodium - (chloride + bicarbonate)
Because serum albumin is a major unmeasured anion, many calculators also provide a corrected anion gap. This matters when albumin is low, since the uncorrected number may hide clinically important acid-base abnormalities. The albumin adjustment improves the accuracy of the interpretation and makes the result more useful for risk assessment.
A calculator is especially useful when reviewing lab results during emergency or complex cases. It can signal a possible anion deficit or a pattern consistent with hidden acid-base trouble. Even so, the number should always be interpreted with the rest of the blood work, symptoms, and overall clinical picture.
Normal, Elevated, and Low Anion Gap Results
A standard anion gap often suggests the balance between measured electrolytes is within the expected expected range. Yet, a normal result does not always rule out disease. Sometimes, there may still be metabolic acidosis if the body is losing bicarbonate and replacing it with chloride, which leads to a typical anion gap finding.
A high anion gap metabolic acidosis suggests that unmeasured acids are accumulating in the blood. This result often prompts a search anion gap in chronic kidney disease for the main source of acid. A high result is not a diagnosis by itself, but it is a strong clue that something is affecting the body's acid-base system.
A low anion gap is uncommon and can occur with laboratory issues, low albumin, or unusual blood chemistry patterns. Because the calculation depends on the measured electrolytes, a low result should also be reviewed carefully in context. The key point is that both high and low values require thoughtful interpretation rather than simple conclusions.
Reasons Why Hidden metabolic acidosis Can Be Missed Easily
Metabolic acidosis can be hard to detect, especially early on or when the body partially adjusts. One reason it is missed is compensatory hyperventilation, which decreases carbon dioxide and can make the patient appear just mildly unwell at first. Another reason is a mixed acid-base disorder, where one abnormal process counterbalances another and the final numbers look less severe than expected.
Clinical symptoms may also be non-specific. Exhaustion, queasiness, low energy, or mild confusion can be overlooked or attributed to another problem. That is why the anion gap is valuable as a clue in the setting of suspected metabolic acidosis. It can reveal hidden acid gain even when the patient is not obviously unstable.
The anion gap is especially important because it can show an abnormality before the full clinical picture becomes obvious. In that sense, it works as a useful screening tool for acid-base disorders. When combined with labs and bedside findings, it supports better clinical correlation and improved diagnosis.
Main Causes of a High Anion Gap
Various conditions can result in a high anion gap metabolic acidosis. One major cause is lactic acidosis, in which lactate builds up when tissues do not get enough oxygen or when metabolism is stressed. Another common cause is ketoacidosis, which can occur with diabetes, starvation, or heavy alcohol use. Under these conditions, acid production rises and pushes the gap upward.
Renal failure can also cause a high anion gap because the kidneys cannot remove acid efficiently. With worsening kidney function, acids and other retained solutes contribute to the elevation. This makes for kidney-related acid-base changes an important part of any serum chemistry review.
Toxic alcohols are another important cause. Substances such as methanol or ethylene glycol can generate dangerous acid metabolites and produce a large gap. In certain cases, the osmolar gap may also be elevated, which provides another clue that a toxic ingestion may be involved. Because these causes can be life-threatening, the result should be interpreted rapidly and in context.
Adjusting for Albumin and Why It’s Important
Hypoalbuminemia can make the measured anion gap look falsely normal or only mildly elevated. Since albumin possesses a negative charge, lower albumin decreases the baseline gap. That means an significant acid-base problem may be hidden unless a corrected anion gap is calculated.
The idea behind albumin correction is straightforward: if albumin is low, the reported gap should be adjusted upward to better reflect the true acid burden. This improves acid-base interpretation and helps reveal hidden metabolic acidosis. In other words, the corrected value may uncover clinically important unmeasured anions that were not obvious in the raw number.
For this reason, albumin should be considered whenever the anion gap does not fit the clinical picture. A normal-looking result in a patient with low albumin may still mask a real acid-base abnormality. The corrected value provides a more accurate perspective for understanding the patient's serum chemistry and overall status.
How anion gap Fits with interpreting blood gases
The anion gap measurement is more revealing when combined with an arterial blood gas. The blood gas provides direct information about pH, PaCO2, and bicarbonate, while the anion gap helps determine whether the problem reflects acid accumulation. Working together, they give a better picture of the acid-base state.
If the pH is low and bicarbonate is reduced, metabolic acidosis is likely. The PaCO2 can show whether respiratory compensation is occurring, such as through faster breathing to expel carbon dioxide. If the anion gap is high, that points toward a gap-producing disorder rather than plain bicarbonate loss.
In many cases, the blood gas and anion gap should be read together rather than separately. A patient may have an abnormal gap with only mild changes on the gas, or vice versa. That is why clinical correlation matters: the numbers need to match the patient's condition, symptoms, and broader diagnostic context.
Constraints of the Tool
Although a well-designed calculator has limitations. Laboratory variability can affect the result because different instruments and methods may produce slightly different electrolyte values. Minor differences in sodium, chloride, or bicarbonate can change the final gap enough to affect analysis.
Analytical error can also play a role. A single unexpected result may reflect collection or processing issues rather than a true physiologic change. That is why the anion gap should not be used in isolation. It is only one part of the overall evaluation.
The calculator does not replace the broader workup for acid-base problems. The osmolar gap, other chemistry values, and clinical findings may be necessary to identify toxic ingestions, kidney problems, or other causes. In the end, the value is best viewed as a helpful diagnostic aid that still requires careful clinical correlation.
When to Get Medical Help
Abnormal anion gap results should be taken seriously when they occur with warning symptoms. These may include worsening weakness, persistent vomiting, severe dehydration, or signs that the body is struggling to maintain normal acid-base balance. Because the anion gap can be linked to serious disease, prompt evaluation may be necessary.
Confusion and difficulty breathing are especially important warning signs. Confusion can reflect worsening acid-base disturbance, poor perfusion, or toxin exposure. Shortness of breath may signal compensatory hyperventilation or another emergency process. In these situations, immediate medical attention is appropriate rather than waiting for repeat testing.
If a person has abnormal lab results along with symptoms, the next step is typically clinician review and additional testing. The anion gap is useful for early detection, but it does not replace medical judgment. Rapid assessment is especially important when toxic alcohols, severe lactic acidosis, or advanced renal failure are possible.
Commonly Asked Questions
What is anion gap calculator used for?
An anion gap calculator is used to rapidly calculate the anion gap from standard lab values and assist detecting possible acid base disorders. It is especially useful for spotting hidden metabolic acidosis, measuring unmeasured acids, and supporting further interpretation of lab results. When albumin is included, it can also improve the accuracy of the corrected anion gap.
How should you read a high anion gap mean in metabolic acidosis?
A high result usually implies that excess acids are rising in the body, creating high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The number is a sign that should be compared with blood gas findings, symptoms, and the rest of the electrolyte data.
How can you correct the anion gap for low albumin?
When hypoalbuminemia is present, the measured gap may be falsely low. A corrected anion gap adjusts the result upward to account for reduced albumin. This albumin adjustment helps refine acid-base interpretation and can reveal a hidden gap that was masked by low protein levels.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A normal anion gap can still occur in metabolic acidosis, especially when bicarbonate loss is Find out more balanced by an increase in chloride. This is often called normal anion gap, or hyperchloremic, metabolic acidosis. That is why the result must be interpreted with the rest of the serum chemistry and not used alone.
Which conditions may cause a low or high anion gap?
A high anion gap can result from lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A low anion gap may occur with hypoalbuminemia, lab issues, or less common blood chemistry patterns. Because both are influenced by the full electrolyte panel, the result should always be reviewed with clinical correlation.
At what time should abnormal anion gap results be evaluated urgently?
Abnormal results should be evaluated urgently when they occur with urgent symptoms such as confusion, shortness of breath, marked weakness, or evidence of poisoning. If the abnormal gap occurs alongside a low pH, altering PaCO2, or worrisome arterial blood gas measurements, immediate medical care may be needed. An abnormal anion gap can be a helpful warning sign, but severe symptoms should never be ignored.