An anion gap calculator is a handy diagnostic tool for assessing acid-base status, especially when a patient has metabolic acidosis. It can reveal whether the body has too many unmeasured anions, which can indicate a specific metabolic derangement and guide clinical assessment. When used properly, the anion gap is more than a single number: it is part of a larger interpretation that includes serum chemistry, blood gas results, and the body’s compensatory response.
This guide outlines what the anion gap measures, how to calculate it, how to interpret normal anion gap versus elevated anion gap findings, and how to evaluate acid-base compensation with support from Winter's formula. It also covers albumin correction, which is essential when serum albumin is low, and reviews common causes such as lactic acidosis, ketoacidosis, renal failure, and toxins.
What the Anion Gap Measures
The anion gap indicates the association between observed electrolytes in the blood, especially sodium, chloride, and bicarbonate. Put simply, it calculates the gap between the main measured cations and anions in serum chemistry. Because the body must remain electrically neutral, the gap suggests the presence of unmeasured anions when it is elevated.
In clinical practice, the anion gap is used to help classify metabolic acidosis. A high result often suggests accumulation of acids that are not directly measured on a standard panel. A normal result, on the other hand, may suggest bicarbonate loss balanced by a rise in chloride. This is why the anion gap is so useful in interpretation of acid-base disorders.
The anion gap is not a direct measurement of a single substance. It is a calculated value that provides insight into electrolyte balance and hidden metabolic changes. Because the calculation depends on laboratory values, even small shifts in sodium, chloride, and bicarbonate can change the result and affect the diagnostic picture.
How to Use an Anion Gap Calculator
An anion gap calculator simplifies the arithmetic, but you still need the correct inputs. The calculator typically requires serum sodium, serum chloride, and serum bicarbonate. Some versions also include potassium. Once those numbers are entered, the calculator returns the anion gap and may help with initial interpretation.
To use the tool well, enter values from the same blood draw whenever possible. Mixing values from different times can affect the calculation and reduce diagnostic accuracy. If the result is unexpectedly high or low, check the underlying laboratory values first. A calculator is practical anion gap example only as accurate as the data provided.
Here is the simple workflow:
- Enter the serum sodium value from the chemistry panel. Input the serum chloride value. Input the serum bicarbonate value, sometimes reported as total CO2. If the calculator includes it, add potassium. Examine the calculated value and compare it with the appropriate reference interval.
The best use of the calculator is not just to get a number, but to connect that number to the patient’s acid-base status. If a blood gas shows acidemia or alkalemia, the anion gap can help determine whether the process is straightforward or part of a mixed disorder.
Formula for Anion Gap & Step-by-Step Calculation
A standard anion gap formula is:
Anion gap = Na - (Chloride + Bicarbonate)
Some clinicians also use K in the equation:
Anion gap = Sodium + Potassium - (Cl + Bicarbonate)
The potassium-added version tends to produce a slightly higher number, but most clinical references prefer the simpler formula without it. Whichever version is used, the key is uniformity in clinical assessment and review.
Example calculation using the simpler formula:
- Serum sodium = 140 Serum chloride = 102 Serum bicarbonate = 24
Computation:
140 - (102 + 24) = 14
The result must then be compared with the expected reference interval for the lab being used. Various analyzers and methods can change the normal anion gap range slightly, which is why site-specific values matter.
Albumin also matters because it is a major unmeasured anion. When albumin is low, the apparent anion gap may be inappropriately normal or only mildly elevated despite significant acid retention. This is why the raw calculation is only the first step, not the last result.
Standard Anion Gap compared with Increased Anion Gap
A standard anion gap usually suggests that bicarbonate has been removed and replaced by chloride, resulting in a hyperchloremic picture. This is still a form of metabolic acidosis, but it is distinct from the picture seen when acids accumulate and produce an increased anion gap.
An increased anion gap indicates excess undetected anions. This often signals acids such as lactate, ketones, or toxic metabolites. In other words, the body’s measured electrolytes do not fully describe the drop in bicarbonate, so hidden acids are likely contributing.
Understanding the distinction improves interpretation and helps focus the differential diagnosis. A normal gap can suggest bicarbonate loss from the gastrointestinal tract or kidneys, while an elevated gap suggests more strongly to acid accumulation. Both patterns can produce acidemia, but their causes and management are different.
The reference range varies by lab, but a commonly used normal range is roughly 8 to 12 or 10 to 14, depending on the method. Always read the result using the lab’s own interval, and do not rely on a single cutoff without context.
How to Interpret Acid-Base Balance
Once the anion gap points to a metabolic problem, the next step is to check acid-base compensation. The body often compensates to metabolic acidosis with respiratory compensation, raising ventilation to lower carbon dioxide and somewhat correct the pH. This is an expected compensatory response, but it has boundaries.
A blood gas helps determine whether the primary problem is acidemia or alkalemia and whether compensation is appropriate. The pH tells you the direction of the disturbance, while bicarbonate and carbon dioxide help reveal the mechanism. If the pH is low and bicarbonate is low, a metabolic process is likely present. If the respiratory response is not what you predict, consider a mixed disorder.
Winter's formula is commonly employed to estimate expected respiratory compensation in metabolic acidosis. A typical version is:
Expected pCO2 = 1.5 × bicarbonate + 8, with a range of about ±2
If the measured pCO2 falls outside the expected range, compensation may be inappropriate or another acid-base process may be present. For example, a higher-than-expected pCO2 suggests concurrent respiratory acidosis, while a lower-than-expected pCO2 suggests additional respiratory alkalosis. This step is essential for recognizing a mixed disorder.
Acid-base interpretation is strongest when the anion gap, pH, bicarbonate, and blood gas all agree. The calculator provides the anionic clue, but the full pattern confirms whether the disturbance is simple or complex.
Modifying the Anion Gap with Albumin
Albumin correction is necessary because serum albumin is a major determinant to the anion gap. If albumin is low, the measured anion gap can underestimate the true burden of unmeasured anions. That is especially important in unstable patients or anyone with malnutrition, inflammation, or liver disease.
Hypoalbuminemia can make an elevated anion gap appear deceptively normal. In practice, this means a patient may have marked acidosis even though the calculator result does not look abnormal. Correcting for albumin improves diagnostic precision and strengthens clinical evaluation.
A commonly used adjustment applies about 2.5 mEq/L to the anion gap for each 1 g/dL albumin below 4 g/dL. This gives the corrected anion gap, which better represents the true metabolic picture. The exact correction method may vary, but the principle remains the same: low albumin decreases the measured gap.
For example, if the anion gap is 12 and serum albumin is 2 g/dL, the corrected anion gap may be roughly 17. That difference can shift interpretation from unremarkable to elevated and reveal an underlying high-gap process. In this way, albumin correction improves detection of hidden metabolic derangement.
Main Causes of Elevated Anion Gap Metabolic Acidosis
An elevated anion gap in the setting of acidotic state usually suggests buildup of acid from one of several major categories. These causes are often remembered as part of a systematic differential, and the pattern can be narrowed with the blood gas, history, and other laboratory values.
Acidosis from lactate occurs when lactate builds up due to tissue reduced blood flow, severe infection, seizures, hypoxia, or other stress states. Because lactate is an unmeasured anion, it widens the gap and decreases bicarbonate.
Acidic ketone buildup is another classic cause. It may occur with diabetes, alcohol use, or prolonged fasting. Ketone bodies are acid-producing and generate an elevated gap that often matches worsening acidemia.
Kidney failure can also lead to an elevated gap because the kidneys cannot excrete acid effectively. As acids accumulate, bicarbonate falls and the anion gap rises.
Toxins are an important and sometimes urgent cause to consider. Examples include toxic alcohols and other substances that generate acid metabolites or interfere with normal metabolism. When the story does not fit a common cause, toxin exposure should remain on the list.
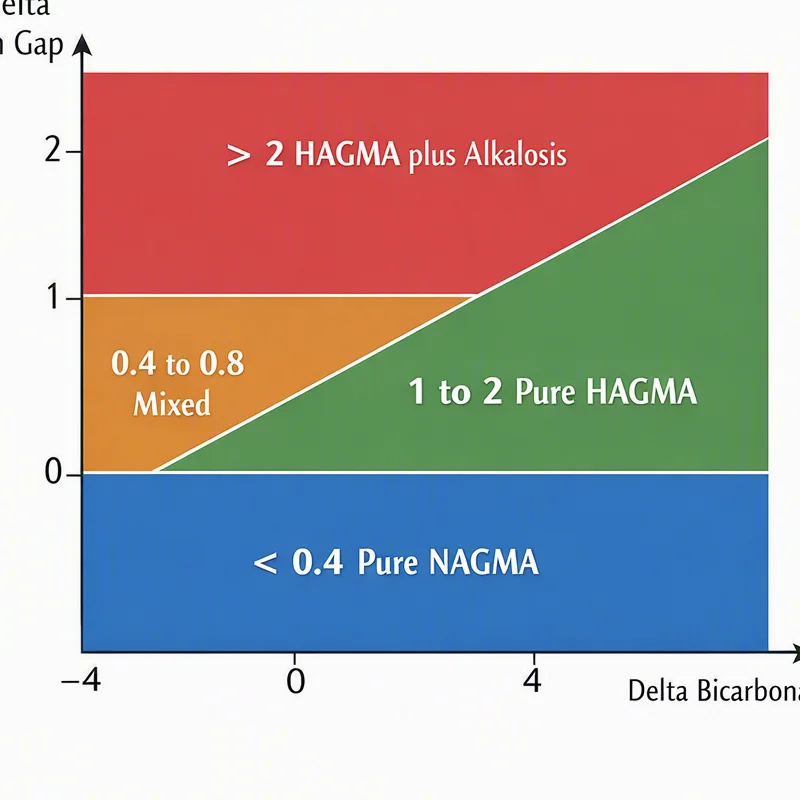
Further clues can come from the delta gap, which compares the change in anion gap to the change in bicarbonate. This can help uncover a combined disorder, such as an elevated-gap acidosis combined with metabolic alkalosis or a concurrent normal-gap acidosis. Using the delta gap provides another layer to the interpretation and enhances better diagnostic accuracy.
In the end, the value of the calculator is not just in classifying the gap, but in linking the result to the patient’s overall acid-base picture. The combination of calculated value, blood gas, pH, and laboratory values gives the clearest view of the underlying problem.
FAQ About Anion Gap and Compensation
What is an anion gap calculator used for?
An Anion Gap Calculator is used to estimate the anion gap from serum chemistry values and help evaluate acid-base problems. It is especially useful in suspected acidotic metabolism, where it can suggest whether excess unmeasured anions are present and whether further evaluation for a high-gap process is needed.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: serum sodium - ( serum chloride + serum bicarbonate). Certain calculations also include potassium. The value is then compared with the lab’s reference interval to determine whether it is normal or elevated.
Why does albumin correction play a role when interpreting the anion gap?
Albumin correction is important because low serum albumin reduces the measured anion gap. In hypoalbuminemia, a patient can have a misleadingly normal number even when a substantial high-gap acidosis exists. Calculating the corrected anion gap enhances interpretation and helps avoid missed diagnoses.
In what way does the anion gap help assess acid-base compensation?
The anion gap identifies whether the metabolic problem is linked to unmeasured acids, while blood gas and pH show how the body is responding. In acid-base compensation, the lungs may reduce carbon dioxide through respiratory compensation. Winter's formula helps determine whether that response is expected or whether a additional process is present.
What conditions commonly cause an elevated anion gap?
Common causes of an elevated anion gap include lactic acidosis, ketoacidosis, renal failure, and certain toxins. These conditions create excess acids or acid metabolites, leading to metabolic acidosis with accumulation of unmeasured anions. A thorough clinical assessment should consider the patient’s symptoms, history, and laboratory values.